

You can hold a job, answer texts, keep a calendar, and still feel your stomach tighten when someone wants more closeness than you can comfortably give. You may even be the person others call calm, independent, or low-maintenance, while privately feeling cornered by emotional talk, confused by conflict, or relieved when plans stay practical and brief. Therapy for Avoidant Attachment starts with naming that pattern without turning it into a character flaw.

Recognizing Avoidant Attachment in Your Daily Life
A client can look highly functioning from the outside and still dread the moment a conversation turns personal. At work, this often shows up as preferring clear tasks over team vulnerability, handling everything alone, and feeling uneasy when someone offers help you didn't ask for. In friendships, it can look like being dependable but hard to know, especially when people start expecting emotional disclosure.
What this pattern can feel like
In romantic relationships, the same person may enjoy connection at a distance and then pull back when things become more intimate. A partner asks, “What are you feeling?” and the mind goes blank, or the body goes tense, or the answer comes out as logic instead of feeling. That doesn't mean the person is cold. It usually means closeness has started to register as pressure, and the nervous system reaches for distance as protection.
Avoidant attachment is best understood as a learned protective strategy, not a defect. Large prevalence studies put avoidant attachment at 23% to 25% of adults, which is about 1 in 4 adults in the available research, and insecure attachment overall at about 40% to 45% of adults outside secure attachment (attachment style statistics). That's one reason therapy for avoidant attachment isn't niche care. Therapists see it often in adult outpatient work.
A useful test is simple. If closeness feels good in theory but crowded in practice, that's worth paying attention to.
What confuses many people is that avoidant patterns can coexist with competence, generosity, and strong problem-solving. Someone may be excellent in crisis, yet feel oddly exposed when a relationship becomes emotionally honest. That mismatch is often what brings people to treatment, not a dramatic collapse.
A better question than “What's wrong with me?” is, “What did this style help me survive?” If the answer is, “It helped me stay self-contained, calm, or less dependent,” then the pattern makes sense. Therapy starts there, with respect for the protection before asking for change.
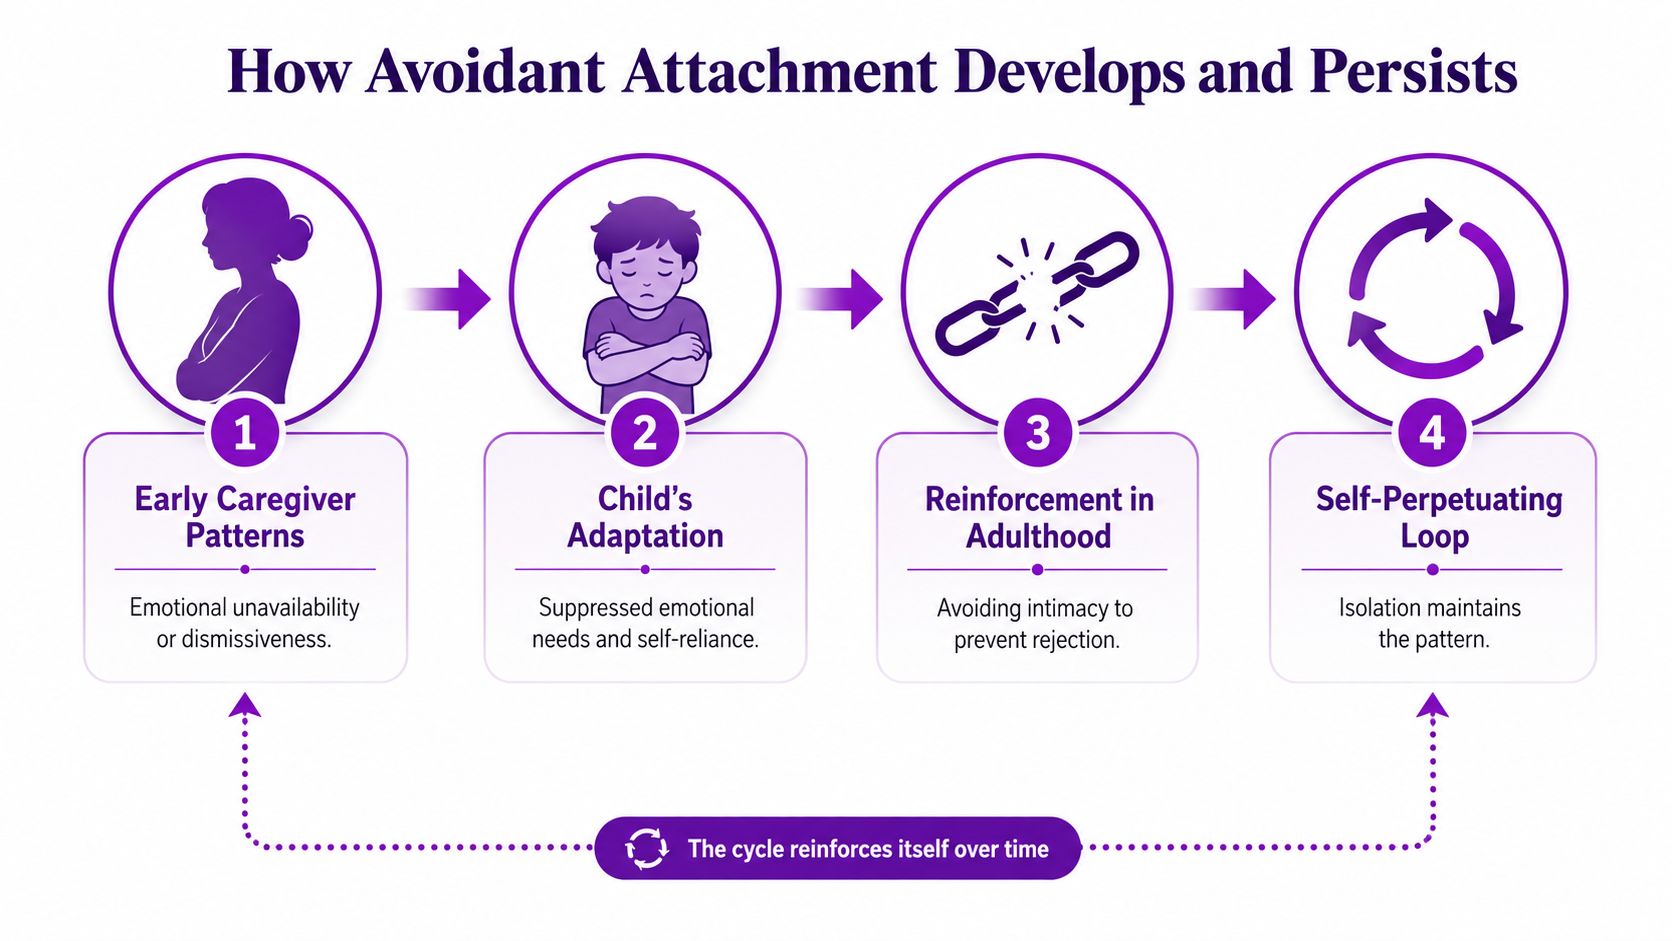
How Avoidant Attachment Develops and Persists
Avoidant patterns usually start as adaptation. When caregivers are emotionally unavailable, dismissive, or inconsistent, a child learns that needing too much can lead to disappointment, interruption, or shame. The child doesn't choose that lesson on purpose. The child's system decides, “Rely on yourself, stay contained, and don't ask for what won't be met.”
Why self-reliance can become a trap
That strategy often works well enough to carry into adulthood. The person becomes skilled at handling logistics, solving problems, and staying composed under stress. But the same strategy can make vulnerability feel like a risk rather than a bridge, especially in relationships that ask for mutual dependence.
A smoke alarm that once saved you from danger might now go off when toast browns. The alarm isn't broken in a moral sense. It's overprotective because it learned a rule too early and kept using it. Avoidant attachment can work the same way, an old safety rule that still fires when someone gets emotionally close.
The important point is that this pattern persists because it's reinforced, not because it's destiny. The adult avoids closeness to reduce discomfort, which brings short-term relief, which teaches the nervous system that distance was the right move. Over time, the mind starts treating that relief as proof.
Practical rule: if openness reliably makes you feel exposed, your system may be prioritizing protection over connection.
Therapists often hear people say, “I'm just private,” or “I don't need much.” Sometimes that's true. Other times it's a well-worn defense that keeps the person out of situations that might bring grief, rejection, or dependency. The difference matters because therapy for avoidant attachment works best when the protective logic is respected instead of argued with.
For a clearer primer on the broader attachment framework, this overview of insecure attachment in psychology is a helpful companion. It places avoidant patterns inside the bigger map of how people learn to relate, rather than treating them as isolated traits.
Evidence-Based Therapeutic Approaches That Work
Not every therapy style fits avoidant clients equally well. Generic advice like “just open up” usually misses the point, because the barrier isn't only insight. It's the felt experience of vulnerability, dependence, and being emotionally seen. That's why the most useful therapies tend to be the ones that work with protection instead of bulldozing through it.
CBT, attachment-focused work, and EFT
Cognitive Behavioral Therapy can help by identifying the thought patterns and behaviors that keep distance in place, then testing new responses through role-playing, problem-solving, and confidence-building. WebMD notes that there are no medications specifically FDA-approved for avoidant attachment disorder, although medication may be used for related anxiety or depression symptoms (WebMD). CBT is often useful when the person wants structure and concrete tools.
Emotionally Focused Therapy works from a different angle. It focuses on relational bonds, emotional awareness, and the pursue-withdraw cycle that often shows up when one person reaches and the other retreats. For couples, that can be especially relevant when avoidance gets activated by conflict or by a partner's need for reassurance.
A 2019 meta-analysis in Psychotherapy Research found that pretreatment attachment was a small-to-moderate predictor of posttreatment outcome, with r = 0.17, d = 0.35, across 32 studies, and 95% CI = [0.13, 0.22] (meta-analysis PDF). That tells us attachment style can matter in therapy, but it doesn't decide the outcome. Avoidant clients can benefit when the treatment matches their actual barriers.
| Approach | Best fit | What it tends to target |
|---|---|---|
| CBT | Clients who want structure | Thought patterns, behavior changes, confidence |
| EFT | Couples and relational cycles | Emotional bonds, vulnerability, attachment needs |
| Attachment-focused therapy | Clients who need pacing and trust | Relational safety, autonomy, corrective experience |
The practical takeaway is simple. Generic talk therapy can help some people, but avoidant patterns often need a therapist who knows how to keep the room steady, collaborative, and not overly intense. If you want a broader clinical view of the attachment-treatment link, this guide to finding the right therapist can help you think in terms of fit, not just credentials.
Finding and Working with the Right Therapist
The first consultation matters more than many people expect. Avoidant clients usually do better when the therapist is clear, calm, and not pushy about disclosure. If you leave the call feeling cornered, overexposed, or subtly judged for being guarded, that's data, not a personal failure.
Questions worth asking before you commit
Start with direct questions about style. Ask how they work with clients who are skeptical of attachment language, emotionally shut down, or slow to trust. Ask what therapy looks like when a client needs autonomy and pacing, because those details tell you whether the therapist can tolerate your pace without taking it personally.
You can also ask about treatment planning. Clinical guidance aimed at avoidant clients emphasizes collaborative decision-making, predictable structure, and not pushing intimacy too quickly. A therapist who invites you into planning is usually making space for your nervous system to stay online instead of bracing for intrusion.
A few practical checks help too:
- Notice the consultation tone: You're looking for curiosity, not pressure.
- Watch how they handle silence: Good therapists don't rush to fill every pause.
- Ask about goals: Clear, step-by-step goals reduce the sense of emotional free fall.
- Track your body after the call: Relief, steadiness, or mild nervousness can be workable. Dread is worth examining.
Some people like to journal between sessions so they can notice shutdown patterns without trying to perform insight in the room. An AI journaling app Sintera can be a practical off-session tool if you want a private place to sort out what you felt, what you avoided saying, and what questions you want to bring next.
How to keep the work from becoming overwhelming
The biggest mistake is treating therapy like a test of how much you can reveal. It's better to treat it like a paced relationship where trust is built through repeated, manageable contact. If you feel the urge to quit after an emotionally loaded session, that doesn't always mean the therapist is wrong. Sometimes it means your protection system is doing its job.
Therapy works better when the therapist helps you name that urge without shaming it. If they can help you stay engaged long enough to make the work collaborative, you're in much better shape than if you're pushed to “be vulnerable” before you feel ready. reVIBE Mental Health also offers therapy with integrated psychiatric support, which can matter when anxiety, depression, or trauma symptoms are part of the picture.
Beyond Talk Therapy EMDR and Integrated Approaches
Some avoidant clients can talk for months and still stay far from the core wound. They intellectualize, explain, analyze, and summarize beautifully, then go home with the same shut-down response when closeness appears. In those cases, therapy often needs another door in, not more pressure through the same one.
When the body is doing the protecting
EMDR can be useful when early relational pain is stored as vivid emotional residue rather than a neat story. It doesn't require a person to narrate everything in perfect detail, which can feel safer for someone who freezes at the idea of prolonged emotional exposure. If you want the mechanics spelled out, this explanation of EMDR therapy gives a plain-language overview.
Somatic approaches can help when avoidance shows up as numbness, tension, or a strong urge to leave the room mentally. The point isn't to force emotion. It's to help the body learn that closeness can be present without danger. That's often a slower process than people want, but it fits how protective systems change.
A review summarized by Meadow notes that the Levy and Johnson 2018 meta-analysis included 36 studies and 3,158 participants and found that avoidance was uncorrelated with general therapy outcome (Meadow summary). Read cautiously, that doesn't mean therapy can't help. It suggests that specialized treatment may matter more than generic support when avoidance is the core issue.
Repeated, low-threat corrective experiences usually matter more than one dramatic breakthrough.
That's why integrated care often makes sense. A person might use CBT for coping skills, attachment-focused therapy for relational patterns, and EMDR or somatic work for older emotional material. The mechanism is gradual. The client gets enough safe contact, enough repair, and enough repetition for the nervous system to stop treating closeness like a threat.
Accessing Therapy in the Phoenix Metro Area
Finding therapy in the Phoenix metro area adds a practical layer to the emotional one. You may be comparing insurance networks, commute time, telehealth options, and how quickly a provider can see you. For avoidant clients, those details matter because too much friction at the start can become an excuse to disappear.
What to look for locally
Start with access. If in-person therapy feels too activating at first, secure online sessions can lower the barrier. If you need medication support along with therapy, integrated practices can reduce the number of separate appointments you have to coordinate.
reVIBE Mental Health serves Chandler, Phoenix Deer Valley, Phoenix PV, Scottsdale, and Tempe, with appointments available seven days a week and both in-person and secure online sessions. Their practice also accepts most major insurance plans and helps with verification, which can make the first step less cumbersome. The listed locations are:
- reVIBE Mental Health – Chandler, 3377 S Price Rd, Suite 105, Chandler, AZ
- reVIBE Mental Health – Phoenix Deer Valley, 2222 W Pinnacle Peak Rd, Suite 220, Phoenix, AZ
- reVIBE Mental Health – Phoenix PV, 4646 E Greenway Road, Suite 100, Phoenix, AZ
- reVIBE Mental Health – Scottsdale, 8700 E Via de Ventura, Suite 280, Scottsdale, AZ
- reVIBE Mental Health – Tempe, 3920 S Rural Rd, Suite 112, Tempe, AZ
Their phone number is (480) 674-9220. If you want a place that combines therapy with psychiatric care, that integrated model can simplify matching and make it easier to stay with treatment when life gets busy or avoidance starts to creep back in.
The first contact should feel straightforward. You should be able to ask about fit, availability, insurance, and whether the provider understands avoidant attachment without having to perform a perfect explanation of your history. If the environment feels welcoming and the process feels organized, that already helps reduce the sense that therapy is another system you have to manage alone.
Common Concerns About Starting Therapy
Many avoidant adults don't avoid therapy because they hate growth. They avoid it because they don't want to be cornered into a style of relating that feels intrusive, messy, or emotionally performative. That's a reasonable concern, and it deserves a straight answer.
What usually worries people most
Therapy should not force you to spill your whole life in the first session. Good therapy respects pacing, and with avoidant attachment that matters even more. If a therapist keeps pushing for depth before trust is built, your urge to withdraw is predictable, not stubborn.
Another common fear is, “What if I don't feel anything?” That happens. Some people come in numb, detached, or very intellectual. The work then becomes less about hunting for tears and more about noticing the body, the defenses, and the moments when your system starts to brace.
You may also worry that change means becoming needy or overly emotional. That's not the goal. The goal is flexibility, the ability to stay connected without losing yourself and to set distance without disappearing.
You don't have to become a different personality to benefit from therapy.
Long-standing patterns can change, but they usually shift through repetition, not revelation. That means a therapist's steadiness, your willingness to stay engaged, and a plan that fits your style matter more than dramatic breakthroughs. If you're high-functioning and skeptical, that's not a barrier. It's information the therapist should work with.
You don't need to wait until avoidance has damaged every relationship. If your pattern is costing you ease, closeness, or the ability to ask for help when it matters, therapy can be a strategic move rather than a last resort.
If you're in Arizona and want care that understands avoidance, attachment patterns, and the need for a paced, respectful start, reVIBE Mental Health offers therapy, EMDR, and psychiatry with medication management across multiple Phoenix metro locations. Reach out if you want support that takes your autonomy seriously while still helping you build more room for connection.


